Key Summary:
- Researchers analysed 84,128 people with evidence of M tuberculosis infection.
- One-year TB hazard was 86% lower with TPT in medium-burden settings.
- Protection persisted for up to 13 years in low-burden settings.
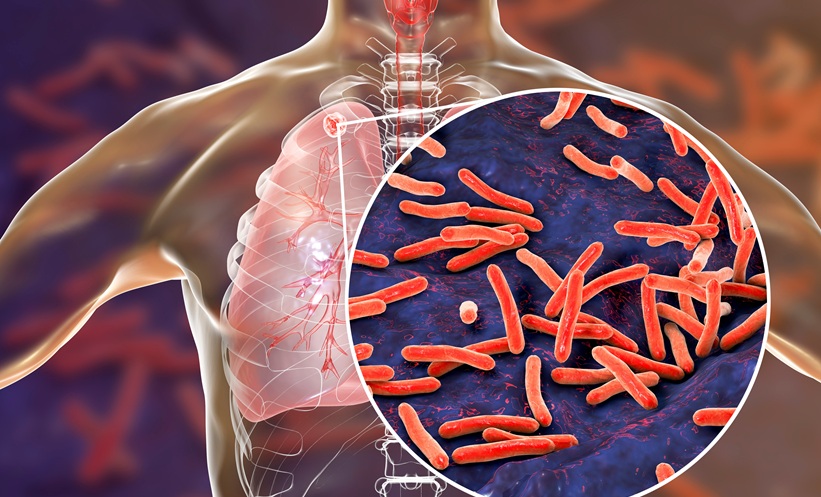
TUBERCULOSIS preventive treatment can provide years of protection for people exposed to tuberculosis, but its durability differs substantially according to background disease burden, a large individual-participant meta-analysis has found.
Among people with evidence of Mycobacterium tuberculosis infection, protection remained strong for years in low- and medium-burden settings but declined considerably faster in high-burden countries.
Researchers conducted a systematic review and individual-participant meta-analysis to investigate how long tuberculosis preventive treatment (TPT) protects close contacts of people with tuberculosis.
Studies were eligible if participants had household or close exposure to a person with clinically or microbiologically diagnosed tuberculosis and had at least 6 months of follow-up.
From 466,523 participants across 47 studies, the final analysis included 84,128 people from 44 cohort studies across 24 countries who had evidence of M tuberculosis infection at baseline.
Countries were classified as low burden if annual tuberculosis incidence was below 20 cases per 100,000 population, medium burden at 20–100 cases per 100,000, and high burden at more than 100 per 100,000.
TPT was strongly protective during the first year, although the magnitude differed between settings.
At 1 year, the adjusted hazard ratio for incident tuberculosis was 0.14 in medium-burden settings (95% CI: 0.09–0.21), corresponding to an estimated 86% lower hazard.
In low-burden settings, the adjusted HR was 0.21 (95% CI: 0.17–0.26), representing approximately 79% lower hazard.
By comparison, the adjusted HR in high-burden settings was 0.57 (95% CI: 0.31–1.07). Because this confidence interval included 1.0, the estimate was less certain.
The most striking differences emerged during longer-term follow-up.
In medium-burden settings, protection remained evident at 8 years, with an adjusted HR of 0.15 (95% CI: 0.07–0.33).
In low-burden settings, evidence of protection persisted for up to 13 years, when the adjusted HR was 0.65 (95% CI: 0.43–1.00).
In contrast, initial protection declined comparatively quickly in high-burden settings. Researchers suggested that ongoing exposure and reinfection could contribute to differences in durability between epidemiological settings.
Treatment completion also influenced early protection. In medium- and low-burden settings, people who completed TPT initially had lower tuberculosis risk than those who did not complete treatment (adjusted HR at 1 year: 0.59; 95% CI: 0.36–0.95).
By 2 years, however, the difference was no longer statistically significant (HR: 0.72; 95% CI: 0.41–1.26), with both groups showing substantial longer-term protection.
The findings suggest that the durability of TPT should not be assumed to be uniform across populations.
Because the analysis pooled observational cohort data and was restricted to close contacts with evidence of M tuberculosis infection, the estimates may not apply equally to other populations receiving preventive treatment.
Nevertheless, the results provide evidence that epidemiological setting is an important consideration when evaluating long-term tuberculosis prevention strategies.
Reference
Linde LR et al. Duration of effectiveness of tuberculosis preventive treatment across various tuberculosis burden settings: a systematic review and individual-participant meta-analysis. Lancet Respir Med. 2026. doi:10.1016/S2213-2600(26)00219-5.
Featured image: Dr_Microbe on AdobeStock
Each article is made available under the terms of the Creative Commons Attribution-Non Commercial 4.0 License.